Anatomopathological Correlation
Another Cause of Acute Cardiogenic Shock
Clinical Case
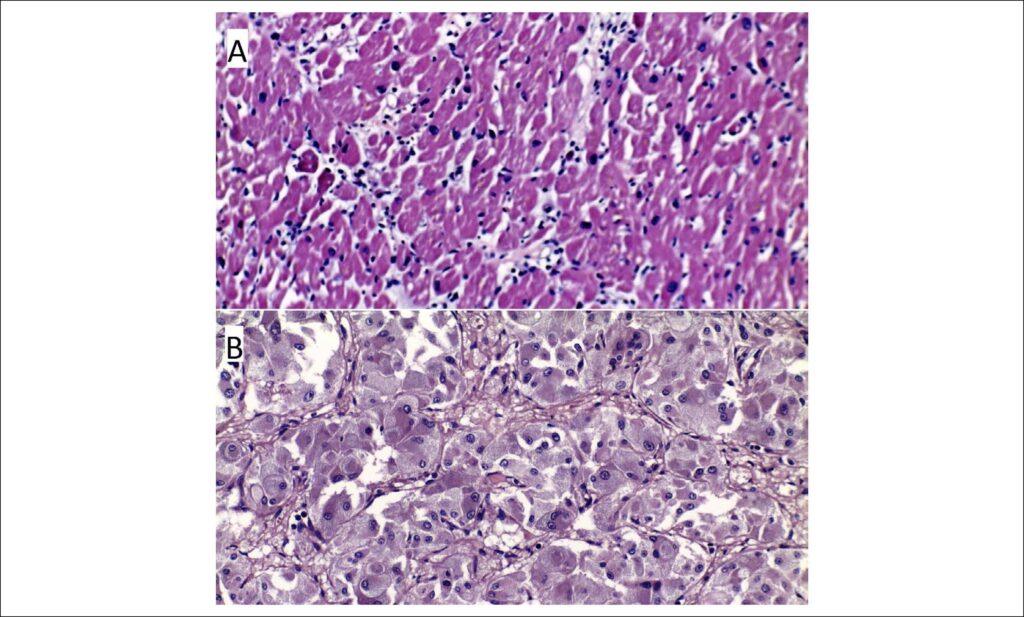
A 64-year-old woman with a history of Diabetes and Hypertension was admitted to the emergency department with acute dyspnea and chest pain. Physical examination revealed hypertension, sinus tachycardia (150 bpm), acute pulmonary edema and poor extremity perfusion. In the context of respiratory failure and hemodynamic instability, she required invasive mechanical ventilation. Blood works showed increased levels of hs-TroponinT (rising from 800 to 1600 ng/L) and the ECG showed poor R wave progression and incomplete right bundle branch block. The echocardiogram revealed a hypertrophied left ventricle, with severe systolic dysfunction and akinetic apical and middle segments. Considering the possibility of acute coronary syndrome, the patient was referred for emergent coronary angiography, which revealed normal coronary arteries. She was admitted to the intensive care unit with the presumed diagnosis of Takotsubo cardiomyopathy. Through the rest of the day, she presented with fluctuating blood pressure and required elevated levels of positive end-expiratory pressure due to pulmonary edema. Despite an apparent favorable evolution, she suddenly developed asystole, refractory to resuscitation efforts, dying less than 24 hours after admission.
[…]
Images
Image gallery fullscreen viewer
Comments are moderated by the editorial team before publication. Discussions should be evidence-based and use scientific language. Conflicts of interest should be declared.