Vinícius C. Fiusa et al. Andrea D. Stephanus Victor F. Couto Gustavo A. Alexim … Thaiene M. M. Severino Ana Claudia C. Nogueira Adriana J. B. A. Guimarães Alexandre Anderson S. M. Soares Elizabeth Bilevicius Vivian Batista Alessandra Staffico Andrei C. Sposito Luiz Sérgio F. de Carvalho
Abstract
Background
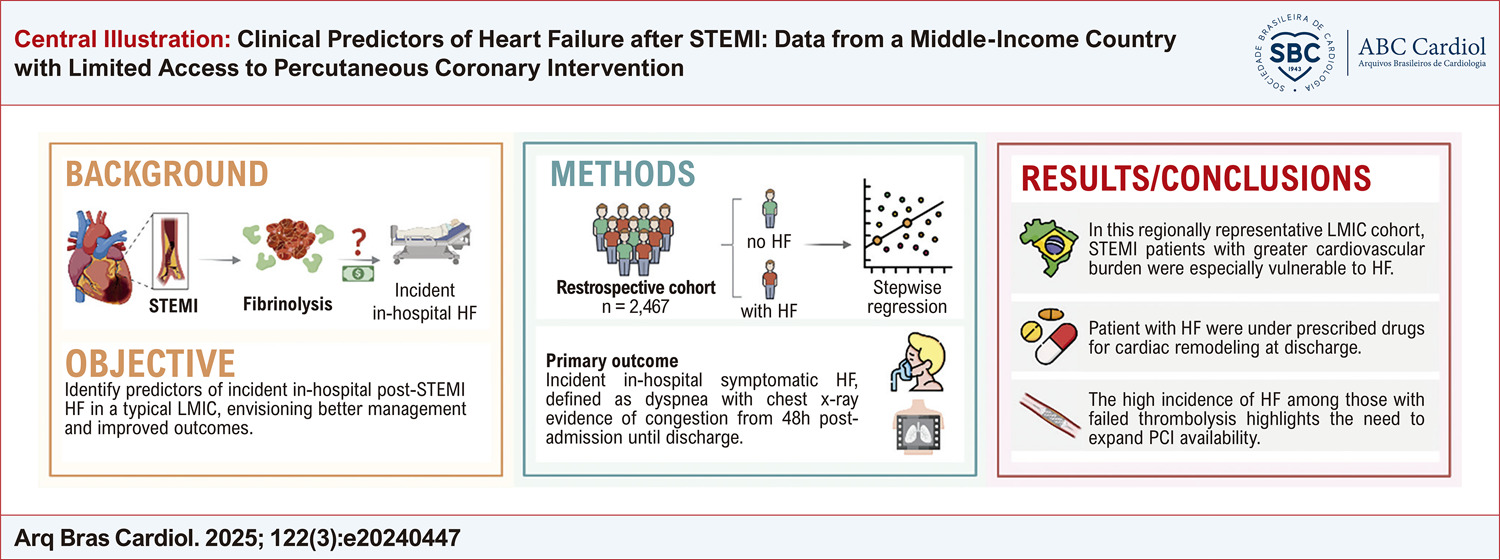
Heart failure (HF) is a common complication of ST-elevation myocardial infarction (STEMI) in low- and middle-income countries (LMICs), where cardiovascular mortality is disproportionately high. Primary percutaneous coronary intervention (PCI) has reduced post-STEMI HF incidence in high-income countries. However, access to this standard of care is poor in LMICs, and data in these settings remain scarce
Objective
To identify predictors of HF following STEMI in a LMIC with limited access to PCI, aiming at better management and outcomes.
Methods
This retrospective cohort study analyzed 2,467 STEMI patients admitted to two Brazilian public hospitals between January/2015 and February/2020. All participants received pharmacological thrombolysis and underwent coronarography within 48h post-admission. The primary outcome was symptomatic HF, defined as dyspnea with chest X-ray evidence of congestion, from 48h post-admission until discharge. Stepwise binary logistic regression was used to identify HF predictors. Significance was defined as p-values<0.05.
Results
The population was 61.9% male, mean age was 58.3±12.6 years, and 39.9% developed post-STEMI HF. HF was more common among older men with cardiovascular-kidney-metabolic (CKM) disease, larger infarcts, and left anterior descending artery involvement. Medications were often underprescribed at discharge, especially aldosterone antagonists (11.0%). HF was notably more frequent among individuals with failed thrombolysis (47.0%).
Conclusions
This regionally representative cohort from a LMIC with limited access to PCI showed that older men with CKM disease are particularly vulnerable to post-STEMI HF, and that HF pharmacotherapy at discharge needs optimization. The high HF incidence among patients with failed thrombolysis highlights the need to expand PCI availability.